




Templates
NIST 800-171 Compliance Checklist: 110 Requirements and SPRS
A NIST 800-171 compliance checklist with all 110 Rev. 2 requirements, their SPRS points, Rev. 3 changes, CMMC status and a self-assessment guide. Free Excel.
A HIPAA compliance checklist for IT teams: 76 controls mapped to 45 CFR, each with the evidence auditors ask for. Free PDF and Excel tracker.


Content writer, trio.so
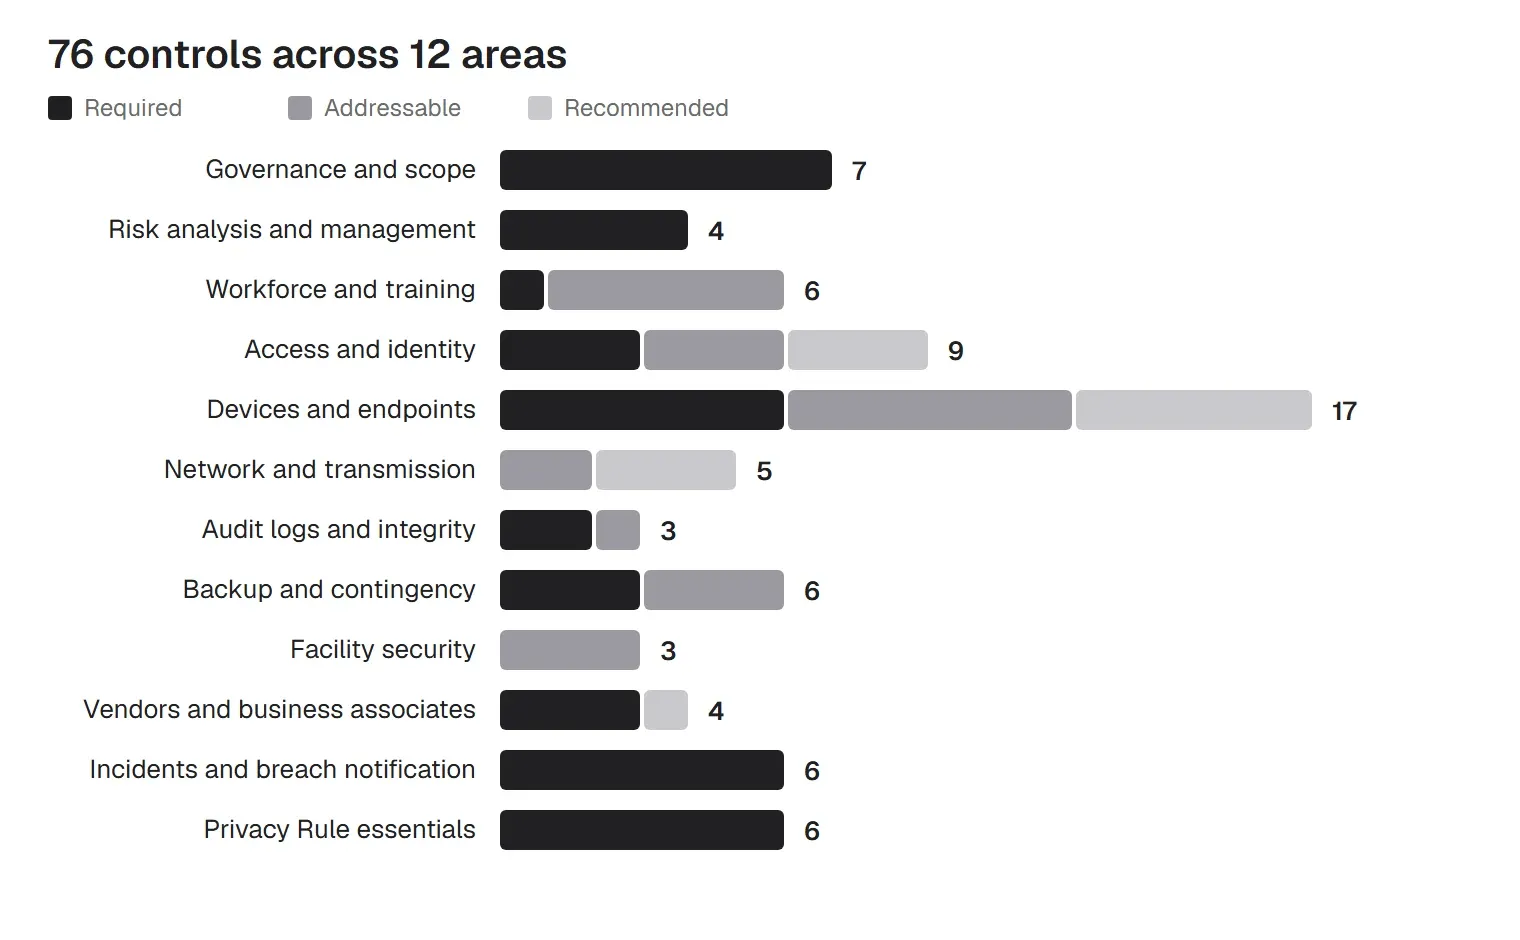
A HIPAA compliance checklist turns the HIPAA Security, Privacy and Breach Notification Rules into a list of jobs you can assign, finish and prove. This one has 76 controls in 12 areas. Each control cites its section of 45 CFR and lists the evidence an auditor will ask for. The PDF and Excel versions add an owner and a frequency for each one.
It is written for the people who carry most of the work: IT managers, sysadmins and MSPs supporting clinics, practices, health tech companies and business associates. The device and endpoint section goes further than most checklists, because that is the part IT actually configures.
Download the checklist as a printable PDF and an Excel tracker with a status dashboard, or work through it below.

In short
If you already know the three rules and the difference between required and addressable, skip to the checklist.
HIPAA applies to covered entities and their business associates. Covered entities are health plans, healthcare clearinghouses and providers who send standard transactions, such as claims, electronically. Business associates are vendors that create, receive, store or send PHI for them. That can include IT providers, MSPs and cloud services that have access to PHI. If you are not sure which you are, see our guide to HIPAA compliance for small business.
A complete checklist covers three rules:
Each Security Rule specification is either required or addressable. Required means you do it. Addressable means you do it if it is reasonable and appropriate, or you document why not and put an equivalent measure in place. It never means optional (164.306(d)).
There is no official HIPAA certification. HHS says it does not endorse or recognize private certifications. What protects you is a working program and the records to show it.
That is too many controls to start at once, so split them into three phases. The first 30 days cover the items regulators ask about first: the risk analysis, encryption, MFA, business associate agreements and offboarding.
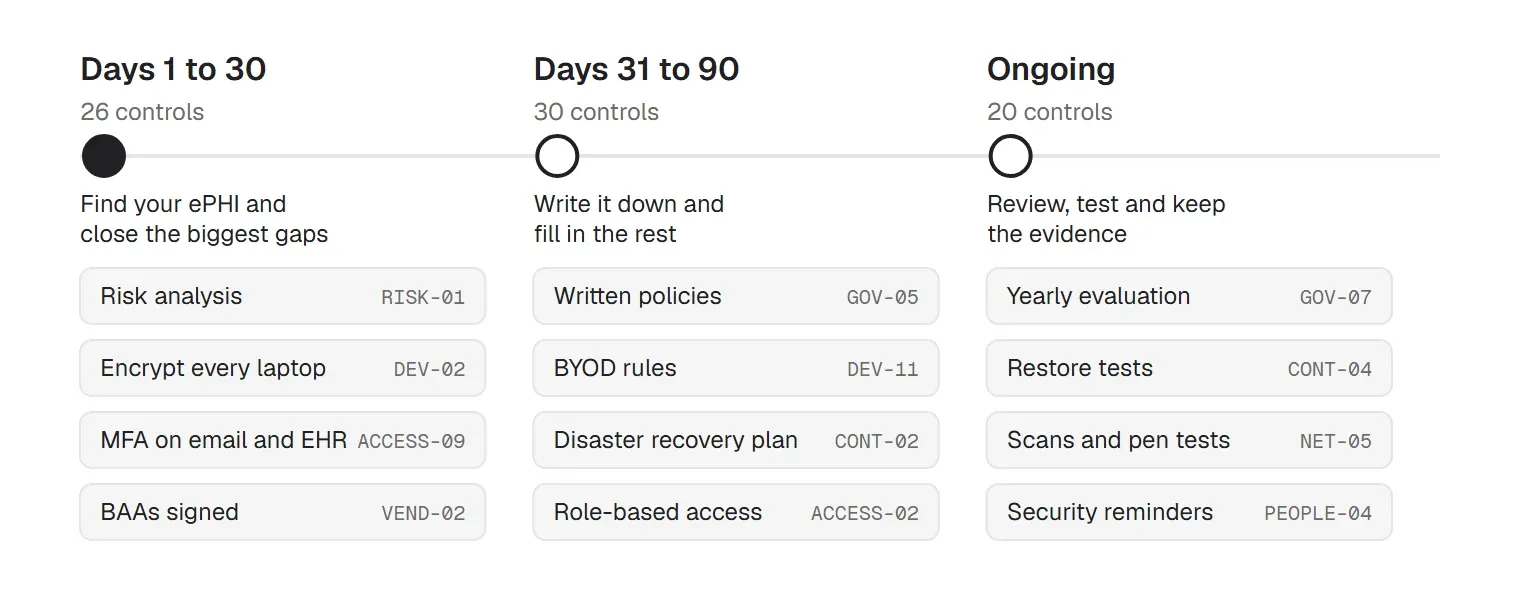
In the Excel tracker, filter the Phase column to see each list. Give every item a named owner and a due date before you start.
Here is the full checklist. Start with the items marked "first 30 days". Required and addressable come from the rule text. Recommended items are not named in the rule, but they are how most teams meet the cited standard, often based on the HHS Cybersecurity Performance Goals. The PDF has the same list with checkboxes, owners and frequencies, and the Excel version adds status tracking.
Someone has to own the program, and you have to know where ePHI lives before you can protect it.
| ID | What to do | 45 CFR | Type | Evidence to keep |
|---|---|---|---|---|
| GOV-01 | Name a security official who owns the Security Rule program (first 30 days) | 164.308(a)(2) | Required | Signed appointment letter |
| GOV-02 | Name a privacy official and a contact person for privacy questions (first 30 days) | 164.530(a) | Required | Appointment letter; contact listed in your Notice of Privacy Practices |
| GOV-03 | Decide in writing whether you are a covered entity, a business associate, or both (first 30 days) | 160.103 | Required | Short determination memo |
| GOV-04 | Map where ePHI is created, stored and sent: systems, devices, cloud apps and vendors (first 30 days) | 164.308(a)(1)(ii)(A) | Required | Data flow map and system list |
| GOV-05 | Write security policies and procedures for every Security Rule standard | 164.316(a) | Required | Policy set with version and approval dates |
| GOV-06 | Keep HIPAA documentation for 6 years from creation or last effective date | 164.316(b)(2)(i) | Required | Retention schedule; archive location |
| GOV-07 | Run a periodic technical and nontechnical evaluation of your safeguards | 164.308(a)(8) | Required | Dated evaluation report |
Everything else builds on the risk analysis. OCR's Risk Analysis Initiative has made it a central issue in its settlements since late 2024. In September 2026, OCR settled with Ambry Genetics for $700,000 after a phishing attack affecting about 225,000 people, citing an inaccurate risk analysis, missing termination procedures and no unique user IDs. Make yours thorough, dated and tied to fixes. Our risk management plan template covers RISK-02.
| ID | What to do | 45 CFR | Type | Evidence to keep |
|---|---|---|---|---|
| RISK-01 | Complete an accurate, thorough risk analysis that covers all ePHI, including laptops, phones, backups and vendors (first 30 days) | 164.308(a)(1)(ii)(A) | Required | Dated risk analysis report with scope |
| RISK-02 | Turn every risk into a fix with an owner and a due date in a risk management plan (first 30 days) | 164.308(a)(1)(ii)(B) | Required | Risk register showing owners, dates and status |
| RISK-03 | Adopt a sanction policy for workforce members who break security rules, and apply it | 164.308(a)(1)(ii)(C) | Required | Sanction policy; sanction records |
| RISK-04 | Review system activity regularly: audit logs, access reports and incident tracking | 164.308(a)(1)(ii)(D) | Required | Review log with reviewer and date |
Many incidents start with a person: a shared password, a phishing click, a laptop left in a car. Training and clear rules lower the odds.
| ID | What to do | 45 CFR | Type | Evidence to keep |
|---|---|---|---|---|
| PEOPLE-01 | Authorize and supervise workforce members who work with ePHI | 164.308(a)(3)(ii)(A) | Addressable | Access approval records |
| PEOPLE-02 | Check that each person's access fits their role before granting it (clearance) | 164.308(a)(3)(ii)(B) | Addressable | Clearance step in onboarding records |
| PEOPLE-03 | Train every workforce member on security and privacy at hire and at least yearly (first 30 days) | 164.308(a)(5)(i); 164.530(b) | Required | Training records and attestations |
| PEOPLE-04 | Send security reminders, such as phishing alerts and policy changes | 164.308(a)(5)(ii)(A) | Addressable | Copies of reminders sent |
| PEOPLE-05 | Monitor login attempts and report discrepancies | 164.308(a)(5)(ii)(C) | Addressable | Failed login report review |
| PEOPLE-06 | Set password rules for creating, changing and protecting passwords (first 30 days) | 164.308(a)(5)(ii)(D) | Addressable | Password policy; enforced settings |
Every person gets their own login, only the access their job needs, and nothing left behind when they leave. Pair this section with our IT offboarding checklist.
| ID | What to do | 45 CFR | Type | Evidence to keep |
|---|---|---|---|---|
| ACCESS-01 | Give every person a unique user ID; remove shared and generic logins (first 30 days) | 164.312(a)(2)(i) | Required | User list with no shared accounts |
| ACCESS-02 | Grant access by role, limited to the minimum necessary for the job | 164.308(a)(4)(ii)(B) | Addressable | Role-to-access matrix |
| ACCESS-03 | Use a documented process to create and change access (joiners and movers) | 164.308(a)(4)(ii)(C) | Addressable | Access tickets with approvals |
| ACCESS-04 | Review who has access to each ePHI system and remove what is no longer needed | 164.308(a)(4) | Recommended | Signed access review |
| ACCESS-05 | Verify the identity of every person or system before it can access ePHI (first 30 days) | 164.312(d) | Required | Authentication settings per system |
| ACCESS-06 | Write an emergency access (break-glass) procedure for ePHI | 164.312(a)(2)(ii) | Required | Procedure and test record |
| ACCESS-07 | Remove all access the day someone leaves: SSO, apps outside SSO, shared accounts, devices, keys (first 30 days) | 164.308(a)(3)(ii)(C) | Addressable | Offboarding checklist with timestamps |
| ACCESS-08 | Keep admin accounts separate from daily user accounts | HHS CPG | Recommended | List of admin accounts |
| ACCESS-09 | Use multi-factor authentication for email, EHR, remote access and admin consoles (first 30 days) | 164.312(d); HHS CPG | Recommended | MFA settings; MFA coverage report |
This is the largest area, and the one most checklists skip. Laptops, desktops, phones and tablets hold or reach ePHI every day, and HHS lists loss or theft of equipment among the five main threats to healthcare organizations. These controls are the technical safeguards an IT team actually configures.
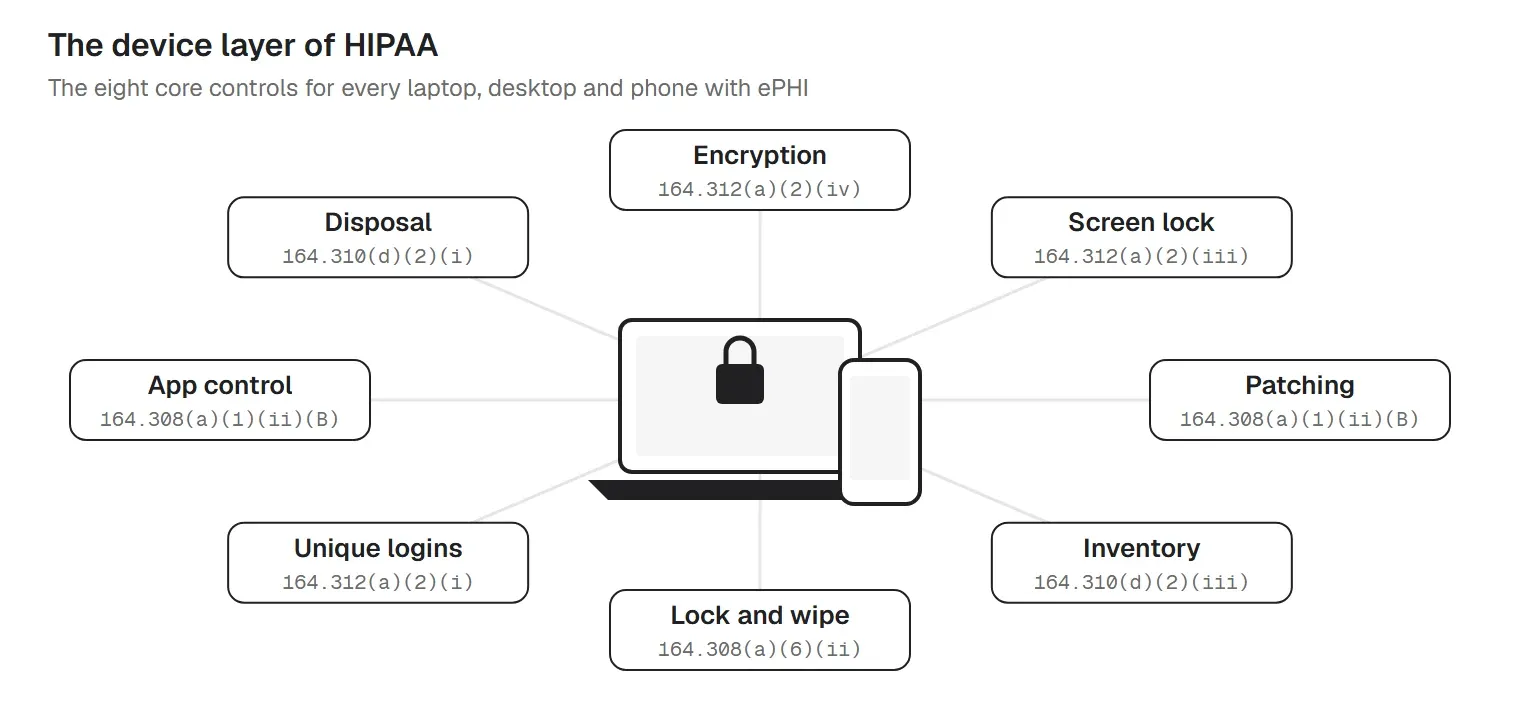
| ID | What to do | 45 CFR | Type | Evidence to keep |
|---|---|---|---|---|
| DEV-01 | Keep a live inventory of every device that touches ePHI: owner, OS version, encryption, last check-in (first 30 days) | 164.310(d)(2)(iii) | Addressable | Inventory export |
| DEV-02 | Encrypt every laptop and desktop (BitLocker, FileVault) and store recovery keys centrally (first 30 days) | 164.312(a)(2)(iv) | Addressable | Encryption status report; key escrow record |
| DEV-03 | Require a passcode on phones and tablets so built-in encryption is active (first 30 days) | 164.312(a)(2)(iv) | Addressable | Passcode compliance report |
| DEV-04 | Lock screens automatically after a set idle time, written in your policy (first 30 days) | 164.312(a)(2)(iii) | Addressable | Screen lock settings per platform |
| DEV-05 | Write a workstation use policy: which devices may access ePHI, where and how | 164.310(b) | Required | Workstation use policy |
| DEV-06 | Physically protect workstations: positioning, privacy screens, locked rooms | 164.310(c) | Required | Walkthrough notes |
| DEV-07 | Patch operating systems and apps on a set timeline, fastest for critical issues (first 30 days) | 164.308(a)(1)(ii)(B) | Recommended | Patch compliance report |
| DEV-08 | Run anti-malware on every endpoint and keep it current (first 30 days) | 164.308(a)(5)(ii)(B) | Addressable | Anti-malware coverage report |
| DEV-09 | Turn on host firewalls and block USB storage where it is not needed | 164.308(a)(1)(ii)(B) | Recommended | Configuration report |
| DEV-10 | Allow only approved apps on devices that hold ePHI | 164.308(a)(1)(ii)(B) | Recommended | Approved app list |
| DEV-11 | Write BYOD rules: whether personal devices may touch ePHI, and the controls they need | 164.310(b); 164.308(a)(1)(ii)(B) | Required | BYOD policy; signed user agreements |
| DEV-12 | Have a lost or stolen device procedure: lock, locate, wipe, then assess for breach (first 30 days) | 164.308(a)(6)(ii) | Required | Procedure; lost device log |
| DEV-13 | Wipe or destroy devices and drives before disposal, and keep proof | 164.310(d)(2)(i) | Required | Wipe record or destruction certificate |
| DEV-14 | Remove ePHI before a device is reissued to someone else | 164.310(d)(2)(ii) | Required | Reissue record |
| DEV-15 | Back up ePHI before moving equipment | 164.310(d)(2)(iv) | Addressable | Backup confirmation |
| DEV-16 | Set a secure configuration baseline for each platform and check for drift | 164.308(a)(1)(ii)(B) | Recommended | Baseline document; compliance report |
| DEV-17 | Replace unsupported operating systems, or isolate them with a documented exception | 164.308(a)(1)(ii)(B) | Recommended | OS version report; exception log |
Encryption is the control that changes the outcome of a loss. HHS breach guidance treats properly encrypted data as secured. If a device was encrypted to that standard and the key was not compromised, a lost laptop usually does not become a reportable breach. A login password is not encryption. Encryption also has to be on before the loss, so check status across the fleet, not one machine at a time.
| Platform | What to turn on | Keys and checks |
|---|---|---|
| Windows | BitLocker (Pro, Enterprise and Education editions; Home has only basic device encryption) | Recovery key stored in your directory or device management tool |
| macOS | FileVault | Personal recovery key stored in your device management tool |
| iOS and iPadOS | Data protection, which turns on with a passcode | Enforce the passcode |
| Android | Encryption, on by default on current devices, plus a screen lock | Enforce the screen lock and a minimum OS version |
| Linux | LUKS full-disk encryption, set at install | Keep the passphrase or key in your vault |
If a device reports encrypted but there is no recovery key in your console, the key was probably never escrowed. Rotate it and store the new one before you need it.
Patching has no fixed deadline in today's rule; it sits under risk management and protection from malicious software. The proposed rule would set one: critical risks within 15 days, high risks within 30. That is a sensible target now. If patches keep missing certain machines, look first at medical imaging workstations or front-desk PCs excluded from your update rings, and at anything still running an unsupported OS. Isolate those and record the exception until they are replaced. Our guide to patch management covers the mechanics.
Personal phones can touch ePHI only if your risk analysis and BYOD policy allow it, and only with the same baseline: a passcode, a supported OS, and a way to remove work data. Write the rules down with our BYOD policy template, and see our guide to HIPAA rules for PHI on mobile devices.
ePHI moving across networks needs the same care as ePHI at rest.
| ID | What to do | 45 CFR | Type | Evidence to keep |
|---|---|---|---|---|
| NET-01 | Encrypt ePHI in transit: TLS for web and email, VPN for remote access (first 30 days) | 164.312(e)(2)(ii) | Addressable | TLS and VPN settings |
| NET-02 | Protect ePHI from being changed in transit without detection | 164.312(e)(2)(i) | Addressable | Integrity control settings |
| NET-03 | Secure Wi-Fi with WPA2 or WPA3, and keep guests on a separate network | 164.308(a)(1)(ii)(B) | Recommended | Wi-Fi configuration |
| NET-04 | Segment the network: keep medical devices, guests and legacy systems apart | 164.308(a)(1)(ii)(B) | Recommended | Network map with segments |
| NET-05 | Scan for vulnerabilities and run penetration tests | 164.308(a)(8) | Recommended | Scan and test reports |
Logs answer the question an investigator asks first: who accessed what, and when.
| ID | What to do | 45 CFR | Type | Evidence to keep |
|---|---|---|---|---|
| AUDIT-01 | Turn on audit logging in every system that holds ePHI: EHR, email, file storage, endpoints (first 30 days) | 164.312(b) | Required | Logging settings; sample log export |
| AUDIT-02 | Set how long logs are kept and protect them from editing | 164.312(b); 164.316(b) | Required | Log retention settings |
| AUDIT-03 | Protect ePHI from improper change or destruction, and be able to prove it | 164.312(c)(1) | Addressable | Integrity controls description |
Ransomware made this section urgent. You need backups you have actually restored, and a plan for running while systems are down. See our disaster recovery plan template.
| ID | What to do | 45 CFR | Type | Evidence to keep |
|---|---|---|---|---|
| CONT-01 | Back up ePHI so you can restore an exact copy (first 30 days) | 164.308(a)(7)(ii)(A) | Required | Backup job reports |
| CONT-02 | Write a disaster recovery plan to restore lost data | 164.308(a)(7)(ii)(B) | Required | Disaster recovery plan |
| CONT-03 | Plan how to keep protecting ePHI while running in emergency mode | 164.308(a)(7)(ii)(C) | Required | Emergency mode plan |
| CONT-04 | Test restores and contingency plans, then fix what failed | 164.308(a)(7)(ii)(D) | Addressable | Test results with date |
| CONT-05 | Rank which applications and data matter most for recovery | 164.308(a)(7)(ii)(E) | Addressable | Criticality list |
| CONT-06 | Allow facility access to restore data during an emergency | 164.310(a)(2)(i) | Addressable | Contingency access procedure |
Physical security still matters for server rooms, front desks and records storage.
| ID | What to do | 45 CFR | Type | Evidence to keep |
|---|---|---|---|---|
| FAC-01 | Write a facility security plan for areas with ePHI systems | 164.310(a)(2)(ii) | Addressable | Facility security plan |
| FAC-02 | Control and validate physical access: badges, keys, visitor logs | 164.310(a)(2)(iii) | Addressable | Badge and visitor logs |
| FAC-03 | Record repairs to physical security: doors, locks, walls | 164.310(a)(2)(iv) | Addressable | Maintenance records |
If a vendor touches PHI, it needs a business associate agreement before the first record moves. That includes your EHR, email, cloud storage, billing service and IT provider.
| ID | What to do | 45 CFR | Type | Evidence to keep |
|---|---|---|---|---|
| VEND-01 | List every vendor that creates, receives, stores or sends PHI for you (first 30 days) | 164.308(b)(1) | Required | Vendor list |
| VEND-02 | Sign a business associate agreement with each one before PHI flows (first 30 days) | 164.308(b)(1); 164.502(e); 164.504(e) | Required | Signed BAAs |
| VEND-03 | If you are a business associate, sign BAAs with your own subcontractors | 164.308(b)(2); 164.314(a) | Required | Subcontractor BAAs |
| VEND-04 | Review each business associate's security safeguards | 164.308(b)(1) | Recommended | Vendor review notes or attestations |
Decide the steps before you need them. Our data breach response plan template covers the full process.
| ID | What to do | 45 CFR | Type | Evidence to keep |
|---|---|---|---|---|
| INC-01 | Write and test an incident response procedure: identify, respond, mitigate, document (first 30 days) | 164.308(a)(6)(ii) | Required | Procedure; incident log |
| INC-02 | Assess every possible breach using the four-factor risk assessment | 164.402 | Required | Completed risk assessments |
| INC-03 | Notify affected individuals without unreasonable delay, and no later than 60 days after discovery | 164.404 | Required | Copies of notices and dates |
| INC-04 | Notify prominent media when a breach affects more than 500 residents of a state | 164.406 | Required | Media notice |
| INC-05 | Notify HHS: at the same time for 500 or more people; yearly log within 60 days of year end for fewer | 164.408 | Required | HHS submission receipts |
| INC-06 | Business associates: report breaches to the covered entity within 60 days, or sooner if the BAA says so | 164.410 | Required | Notice to covered entity |
The Privacy Rule is mostly a job for your privacy official, but IT supports several of these items.
| ID | What to do | 45 CFR | Type | Evidence to keep |
|---|---|---|---|---|
| PRIV-01 | Confirm your Notice of Privacy Practices includes the changes due February 16, 2026, and post it in your office and on your website (first 30 days) | 164.520 | Required | Current notice with date |
| PRIV-02 | Limit uses and disclosures of PHI to the minimum necessary | 164.502(b); 164.514(d) | Required | Minimum necessary policy |
| PRIV-03 | Answer patient access requests within 30 days (one 30-day extension allowed) | 164.524 | Required | Request log with dates |
| PRIV-04 | Run a complaints process, and never retaliate against people who complain | 164.530(d); 164.530(g) | Required | Complaint log |
| PRIV-05 | Get written authorization for uses that need it, such as marketing | 164.508 | Required | Signed authorizations |
| PRIV-06 | Protect PHI in every form, including paper and conversations | 164.530(c) | Required | Walkthrough notes |
When a device goes missing, the first hour matters. The 60-day notification clock starts when the loss is discovered. Agree on these steps in advance:
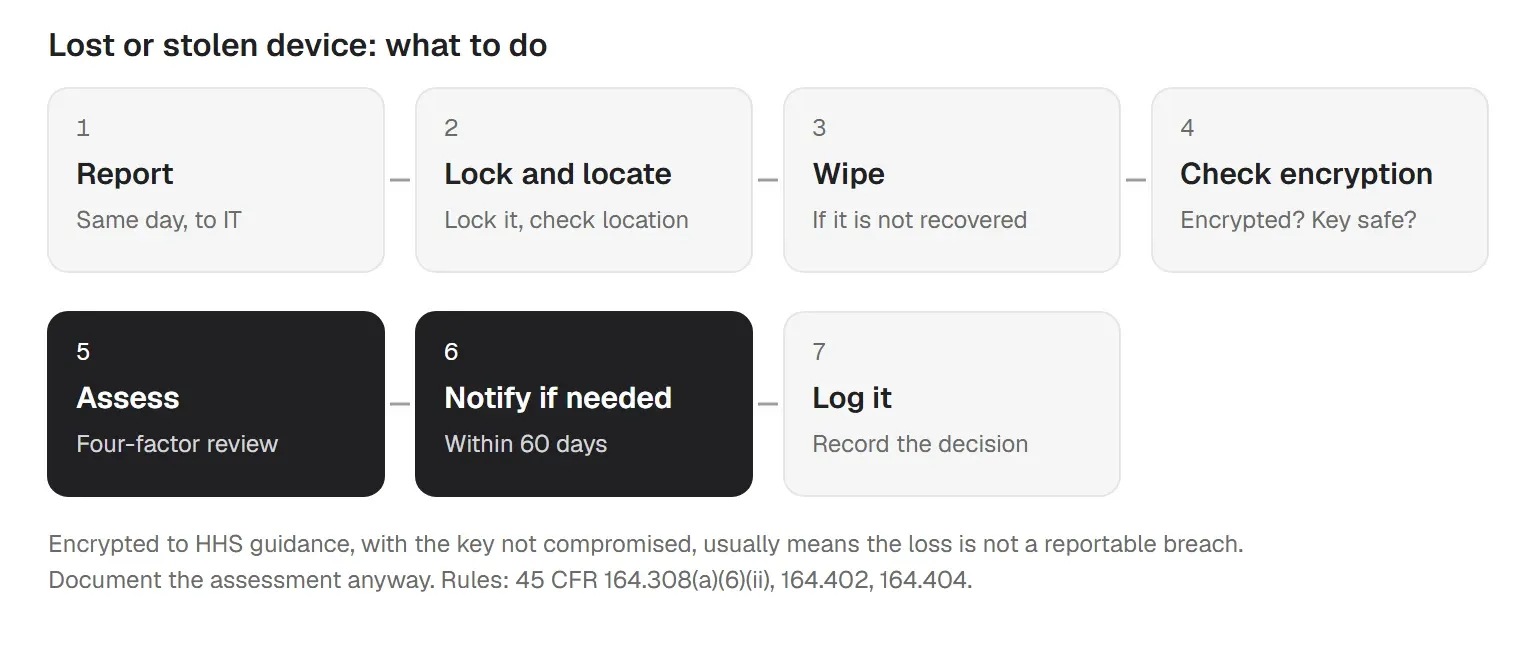

Notices go to affected individuals without unreasonable delay, and no later than 60 days after discovery. Breaches affecting 500 or more people are also reported to HHS at the same time. Smaller breaches go in a yearly log, due within 60 days of the end of the year. If more than 500 residents of one state are affected, prominent media outlets must be notified too.
OCR investigators and outside auditors ask for records, not intentions. Keep these current and dated, and keep them for 6 years (164.316(b); 164.530(j) for Privacy Rule records).
| Control | Evidence | Suggested refresh |
|---|---|---|
| Risk analysis | Dated report covering every system and device with ePHI | Yearly |
| Risk management plan | Risk register with owners, fixes and due dates | Quarterly |
| Device encryption | Encryption status per device, with recovery keys escrowed | Monthly |
| Patching | Patch compliance report by device and severity | Monthly |
| Device inventory | Every device with owner, OS version and last check-in | Quarterly |
| Access reviews | Signed review of who can reach each ePHI system | Quarterly |
| Audit log review | Review record with reviewer, date and findings | Monthly |
| Offboarding | Checklist per leaver with timestamps | Every departure |
| Training | Attendance records and signed attestations | Yearly |
| Business associates | Signed BAA for every vendor on the vendor list | Yearly |
| Backups | Backup reports and the last restore test | Quarterly |
| Incidents | Incident log and breach risk assessments | Every incident |
Generate device reports on a schedule, not on request. A dated monthly encryption and patch report shows a control working over time. A screenshot taken the week before an audit shows only that week.
A HIPAA audit is a review by HHS's Office for Civil Rights (OCR) of whether a covered entity or business associate follows the Privacy, Security and Breach Notification Rules. Most organizations never get a random audit. They meet OCR through an investigation, after a complaint or a breach report. Either way, the request looks much the same.
In 2024, OCR received 30,256 complaints and opened 730 compliance reviews. It started no audits that year, citing a lack of funding. It also investigates every reported breach affecting 500 or more people, and there were 663 of those in 2024. If you report a large breach, expect OCR to ask for your records.
The direction is clear: the next audits look at technical controls, which means the device and access evidence in this checklist.
In the 2016 to 2017 audits, organizations had 10 business days to upload documents. OCR's desk audit guidance asked for the current risk analysis and the one before it, policies as they stood six years before the letter, records from the previous calendar year, and proof that staff could reach the documents and that they were reviewed. Investigation letters set their own deadlines, but they ask for the same kinds of records. The full list of what OCR can test is in its audit protocol.
The most common gap is not a missing policy. It is a missing record that the policy was followed.
The IDs point to the items in the checklist above, and in the PDF and Excel tracker.
| # | Have ready | Checklist IDs | What to have on file |
|---|---|---|---|
| 1 | Name one person to handle OCR letters and track the response deadline | GOV-01, GOV-02 | Named security and privacy officials; a contact for OCR |
| 2 | Your current risk analysis and the one before it | RISK-01, GOV-04 | Both dated, both covering all ePHI: systems, devices, vendors |
| 3 | The risk management plan, and proof the fixes happened | RISK-02 | Each risk with its fix, owner and date, plus the change records or reports |
| 4 | Security, privacy and breach policies, with their history | GOV-05, GOV-06 | Version history going back 6 years |
| 5 | Proof staff can reach the policies and that you review them | GOV-06 | Folder permissions or intranet page, and a review log |
| 6 | Your most recent evaluation of the safeguards | GOV-07 | Dated report, technical and nontechnical |
| 7 | Training and security reminder records for the past year | PEOPLE-03, PEOPLE-04 | Attendance, attestations, reminder emails |
| 8 | Vendor list with a signed BAA for each | VEND-01, VEND-02, VEND-03 | Including subcontractors if you are a business associate |
| 9 | Access reviews, offboarding records and MFA coverage | ACCESS-04, ACCESS-07, ACCESS-09 | Signed reviews, leaver checklists with times, MFA enrollment report |
| 10 | Audit log settings and log review records | RISK-04, AUDIT-01, AUDIT-02 | Retention settings and a dated review log |
| 11 | Device inventory and monthly encryption and patch reports | DEV-01, DEV-02, DEV-07 | Twelve months of dated reports, not one screenshot |
| 12 | Backup reports and the last restore test | CONT-01, CONT-04 | Result and date of the most recent test |
| 13 | Incident log, breach risk assessments and notices for the past year | INC-01, INC-02, INC-03, INC-05 | Including incidents you decided were not breaches |
| 14 | Notice of Privacy Practices and the patient access request log | PRIV-01, PRIV-03 | Current NPP; requests with response dates |
| 15 | Your recognized security practices file | GOV-05, RISK-01, DEV-01 | The framework you follow and 12 months of evidence it was in use |
Since 2021, the law has required OCR to consider whether you had recognized security practices in place for the previous 12 months, such as the NIST Cybersecurity Framework or HHS's 405(d) practices, when it decides on fines and audit outcomes. OCR has said the practices must be "actively and consistently in use", so a policy adopted last month doesn't count. Keep a short file: which framework you follow, and dated evidence from the past year that you followed it. It is not a safe harbor, but OCR must weigh it.
Status in October 2026: proposed, not law. HHS published the proposal on January 6, 2025. The current regulatory agenda lists it as a long-term action, with final action in July 2027. The rule in force today is the existing Security Rule.
The main changes in the proposal:
| Area | What the proposal would require |
|---|---|
| Required vs addressable | The difference goes away; almost every specification becomes required |
| Asset inventory and network map | Written, reviewed at least every 12 months |
| Encryption | ePHI encrypted at rest and in transit, with limited exceptions |
| Multi-factor authentication | Required, with limited exceptions |
| Patching | Critical risks within 15 days, high risks within 30 days |
| Vulnerability scans and pen tests | Scans at least every 6 months; pen test every 12 months |
| Backups and restore | Backups no more than 48 hours old; restore critical systems within 72 hours |
| Compliance audit | Against every Security Rule standard, at least every 12 months |
| Access termination | Notify other regulated entities within 24 hours |
| Business associates | Written verification of safeguards at least every 12 months |
None of this is required yet, and the final rule may differ. Much of it matches what OCR already looks for after an incident. In the PDF and Excel tracker, 22 items are marked "Proposed": they already move you in this direction, so you can build toward it without waiting.
Civil penalties depend on what the organization knew and how fast it fixed the problem. These are the per-violation ranges as adjusted on January 28, 2026, with a calendar-year cap of $2,190,294 for identical violations.
| Culpability | Minimum | Maximum |
|---|---|---|
| Did not know | $145 | $73,011 |
| Reasonable cause | $1,461 | $73,011 |
| Willful neglect, corrected within 30 days | $14,602 | $73,011 |
| Willful neglect, not corrected | $73,011 | $2,190,294 |
For real cases and how fines are set, see HIPAA violation fines and penalties.
More HIPAA guides for IT teams
trio.so covers many of the device controls in this checklist from one console:
Compliance stays your organization's responsibility: the risk analysis, policies, training and agreements are yours to run. What trio.so gives you is control of the device settings this checklist asks for, plus the device reports that show they are working. Learn more about device management for healthcare and compliance automation.
14 day free trial. No credit card required.
Sources. Last reviewed October 2026. This article is for information only and is not legal advice.
Every organization today needs a solution to automate time-consuming tasks and strengthen security. Without the right tools, manual processes drain resources and leave gaps in protection. trio.so is designed to solve this problem, automating key tasks, boosting security, and ensuring compliance with ease.
Every organization today needs a solution to automate time-consuming tasks and strengthen security. Without the right tools, manual processes drain resources and leave gaps in protection. trio.so is designed to solve this problem, automating key tasks, boosting security, and ensuring compliance with ease.





Have questions? We've got answers. This section covers some of the most commonly asked questions related to this topic.
Related
The related industry news, interviews, technologies, and resources.
A NIST 800-171 compliance checklist with all 110 Rev. 2 requirements, their SPRS points, Rev. 3 changes, CMMC status and a self-assessment guide. Free Excel.

A SOC 2 compliance checklist for IT teams: 69 controls mapped to the Trust Services Criteria, with the evidence auditors sample. Free PDF and Excel.

Ten Microsoft Entra conditional access policy templates with what each does, the order to enable them in report-only mode, licensing, and a free download.

SAMA compliance checklist for the SAMA CSF: 4 domains and 32 subdomains, maturity levels 0 to 5, evidence and owners, with a free PDF and Excel tracker.

NCA ECC compliance checklist for ECC-2:2024: all 108 controls by domain, the evidence to keep and the device controls, with a free PDF and Excel tracker.

A NIST compliance checklist for IT teams: 65 controls by CSF 2.0 function, mapped to SP 800-53 and 800-171, with an SPRS calculator. Free PDF and Excel.

Feeling overwhelmed by CCPA? Use this comprehensive CCPA Compliance Checklist to secure customer data on mobile devices. Discover how MDM simplifies compliance.

Need an MDM audit checklist? Our guide covers 7 key areas & compliance strategies to ensure your mobile device management is secure and efficient.
14 day free trial. No credit card required.
trio.so for MSPs: one console, separate clients